Why is the first thyroid surgery considered the most important?
The primary advantage of an initial thyroid procedure is the preservation of clear anatomical landmarks. In surgical practice, a 'virgin' surgical field—one that has not undergone prior intervention—allows the surgeon to identify and protect vital structures with significantly higher precision.
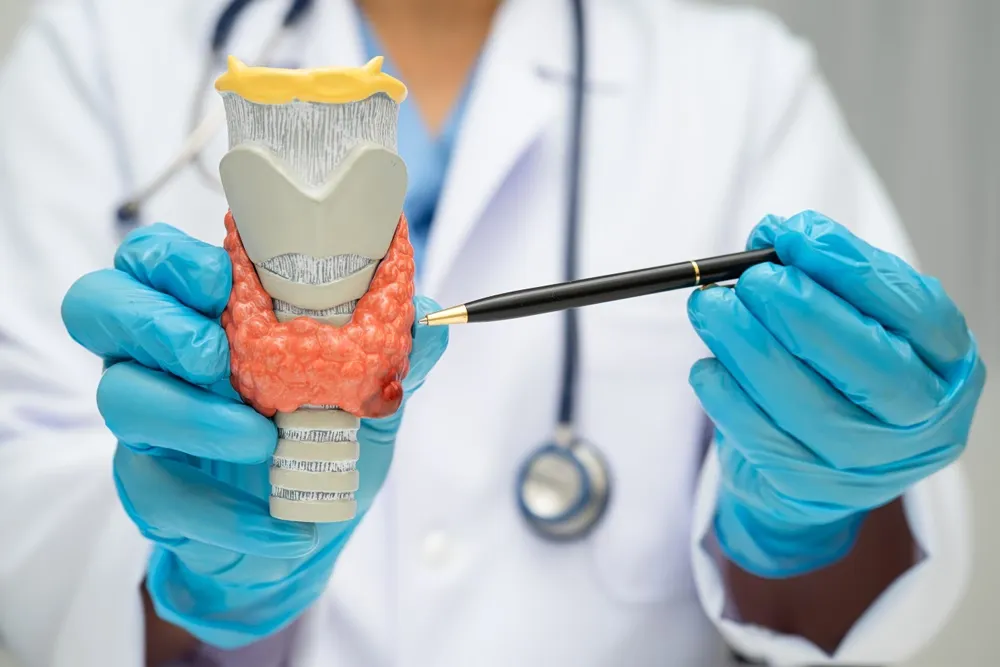
The thyroid gland is located in a relatively small anatomical region: the neck. Despite its compact size, this area contains a high concentration of critical structures that must be preserved to avoid long-term complications. These include:
- The trachea (windpipe)
- Major neck vessels
- The esophagus
- Laryngeal nerves
- Parathyroid glands
When a patient undergoes a subsequent operation (reoperation), the presence of scar tissue (fibrosis) from the first surgery makes the identification of these structures much more difficult. This increased complexity raises both the technical difficulty of the procedure and the potential for post-operative morbidity, making the first surgery the most opportune time to achieve a definitive and safe result.
Do all thyroid conditions require surgical intervention?
Not every thyroid pathology necessitates surgery, as medical management is often a viable alternative depending on the specific diagnosis and patient criteria. Thyroid conditions are broadly categorized into benign and malignant types, each requiring a different clinical approach.
Understanding Benign vs. Malignant Pathologies
Benign conditions often include thyroid nodules, goiters, hyperthyroidism, and various forms of thyroiditis. While these can be serious, they do not always require an immediate operating room visit. In contrast, malignant conditions, specifically thyroid cancer, almost always require a surgical strategy to ensure oncological safety.
The decision to proceed to surgery is based on a rigorous set of criteria. Surgeons must balance the risks of the procedure against the potential benefits of removing the diseased tissue. A successful outcome depends on a foundation of reliable diagnosis and a detailed preoperative investigation to ensure that surgery is truly the most appropriate path for the individual patient.
How is the surgical approach personalized for each patient?
There is no universal surgical template for thyroid diseases; instead, the extent of the procedure must be tailored to the individual's specific diagnosis and anatomical findings. This customization is particularly evident in the choice between different types of thyroidectomies.
For instance, while some patients may require a total thyroidectomy (removal of the entire gland), others may be excellent candidates for a lobectomy (removal of only one lobe). This decision is reached through meticulous preoperative testing and a transparent discussion between the surgeon and the patient regarding the pros and cons of each option.
Navigating Lymph Node Dissection in Cancer Cases
In cases involving thyroid cancer, the question of lymph node clearance becomes a critical component of the surgical plan. Surgeons must determine the appropriate scope of dissection, which involves several complex considerations:
- Whether to perform a central compartment dissection (nodes surrounding the thyroid).
- Whether to extend the clearance to the lateral compartments (nodes near the carotid and jugular vessels).
- Whether the dissection should be unilateral (one side) or bilateral (both sides).
Because these decisions depend on the specific stage and characteristics of the cancer, a standardized approach is impossible. The surgical tactic must be as unique as the patient's own pathology.
Why does surgical experience play such a decisive role?
The surgeon's expertise is a fundamental variable in determining the optimal outcome for thyroid surgery. Because the procedure requires extremely delicate movements and a profound respect for surrounding tissues, the margin for error is minimal.
A specialized thyroid surgeon must possess a mastery of several disciplines: deep anatomical knowledge, proficiency in modern diagnostic methodologies, and precision in contemporary surgical techniques. This level of skill becomes even more critical when dealing with high-complexity cases, such as:
- Giant or retrosternal (descending) goiters.
- Extensive thyroid cancers.
- Complex lymph node dissections.
- Difficult reoperations in scarred fields.
In these scenarios, the surgeon's ability to navigate distorted anatomy while protecting the laryngeal nerves and parathyroid glands is what separates a successful recovery from a high-morbidity outcome.
Can a second surgery be necessary even after a successful first operation?
Yes, the need for subsequent interventions does not necessarily imply that the initial surgery was performed incorrectly or failed to meet medical standards (Lege artis). In some instances, a second procedure is a known clinical possibility due to the nature of the disease itself.
A primary example is the local recurrence of thyroid cancer. Because thyroid cancer can have a high rate of recurrence in the neck, a patient may require further surgery to address new growths. It is essential for patients to understand that a recurrence is a characteristic of the disease's biology and not an automatic reflection of the first surgeon's technical proficiency.
Frequently asked questions
What is the difference between a total thyroidectomy and a lobectomy?
A total thyroidectomy involves the complete removal of the entire thyroid gland. A lobectomy is a more conservative approach where only one lobe of the thyroid is removed. The choice depends on the diagnosis, the size of the nodule, and the risk of malignancy identified during preoperative testing.
Why is scar tissue a problem in reoperations?
Scar tissue, or fibrosis, created during the first surgery obscures the natural anatomical boundaries. This makes it significantly harder for the surgeon to locate and protect vital structures like the parathyroid glands and nerves, thereby increasing the risk of complications during a second procedure.
Does thyroid cancer always require lymph node removal?
Not always. The decision to remove lymph nodes depends on the specific type of cancer, its stage, and whether there is evidence of spread. Surgeons customize the extent of the clearance—whether central or lateral—based on the individual's diagnostic imaging and clinical needs.
Can a surgeon miss something during the first operation?
While surgeons follow strict protocols, the goal of advanced preoperative mapping, such as ultrasound mapping of the neck lymph nodes, is to prevent missing metastases. Thorough diagnostic investigation is designed to ensure the first surgery is as comprehensive as possible to avoid the need for more.
Is a second surgery a sign of surgical failure?
No, a second surgery is not always a sign of failure. In cases like thyroid cancer, local recurrence can occur due to the biological nature of the disease, even if the first operation was performed with perfect technical skill and precision.
Key takeaways
- The first thyroid surgery offers the safest anatomical conditions due to the absence of scar tissue.
- Thyroid surgery must be personalized, choosing between total thyroidectomy and lobectomy based on individual needs.
- Specialized expertise is vital for managing complex cases like giant goiters or cancer dissections.
- The need for reoperation can be caused by disease recurrence rather than surgical error.
Conclusion
Navigating thyroid pathology requires a sophisticated balance of diagnostic precision and surgical skill. While the first operation provides the most favorable environment for protecting vital neck structures, the complexity of the gland demands a highly individualized approach. From selecting the extent of tissue removal to managing the risks of potential recurrence, the focus remains on minimizing morbidity through specialized expertise. Ultimately, the success of thyroid management relies on a combination of thorough preoperative mapping, the surgeon's anatomical mastery, and a clear understanding of the patient's unique clinical profile.